A patient walks in with an MRI report that says “lumbar disc herniation.” That tells us something, but it does not tell us everything.
What we really want to know is what the disc is doing to the person.
Can you sit through a meeting or a drive without constantly changing position? Does bending to put on a shoe send pain into the leg? Can you still train, play golf, work in the yard, or pick up your child without paying for it later? Is the problem mostly in the lower back, or does it travel through the buttock and into the leg?
After approximately 25 years of treating spine and disc-related conditions in Frisco, we have learned that these details often tell us as much about a case as the words on an imaging report. Good herniated disc treatment starts by connecting the anatomy with the patient’s actual symptoms and limitations.
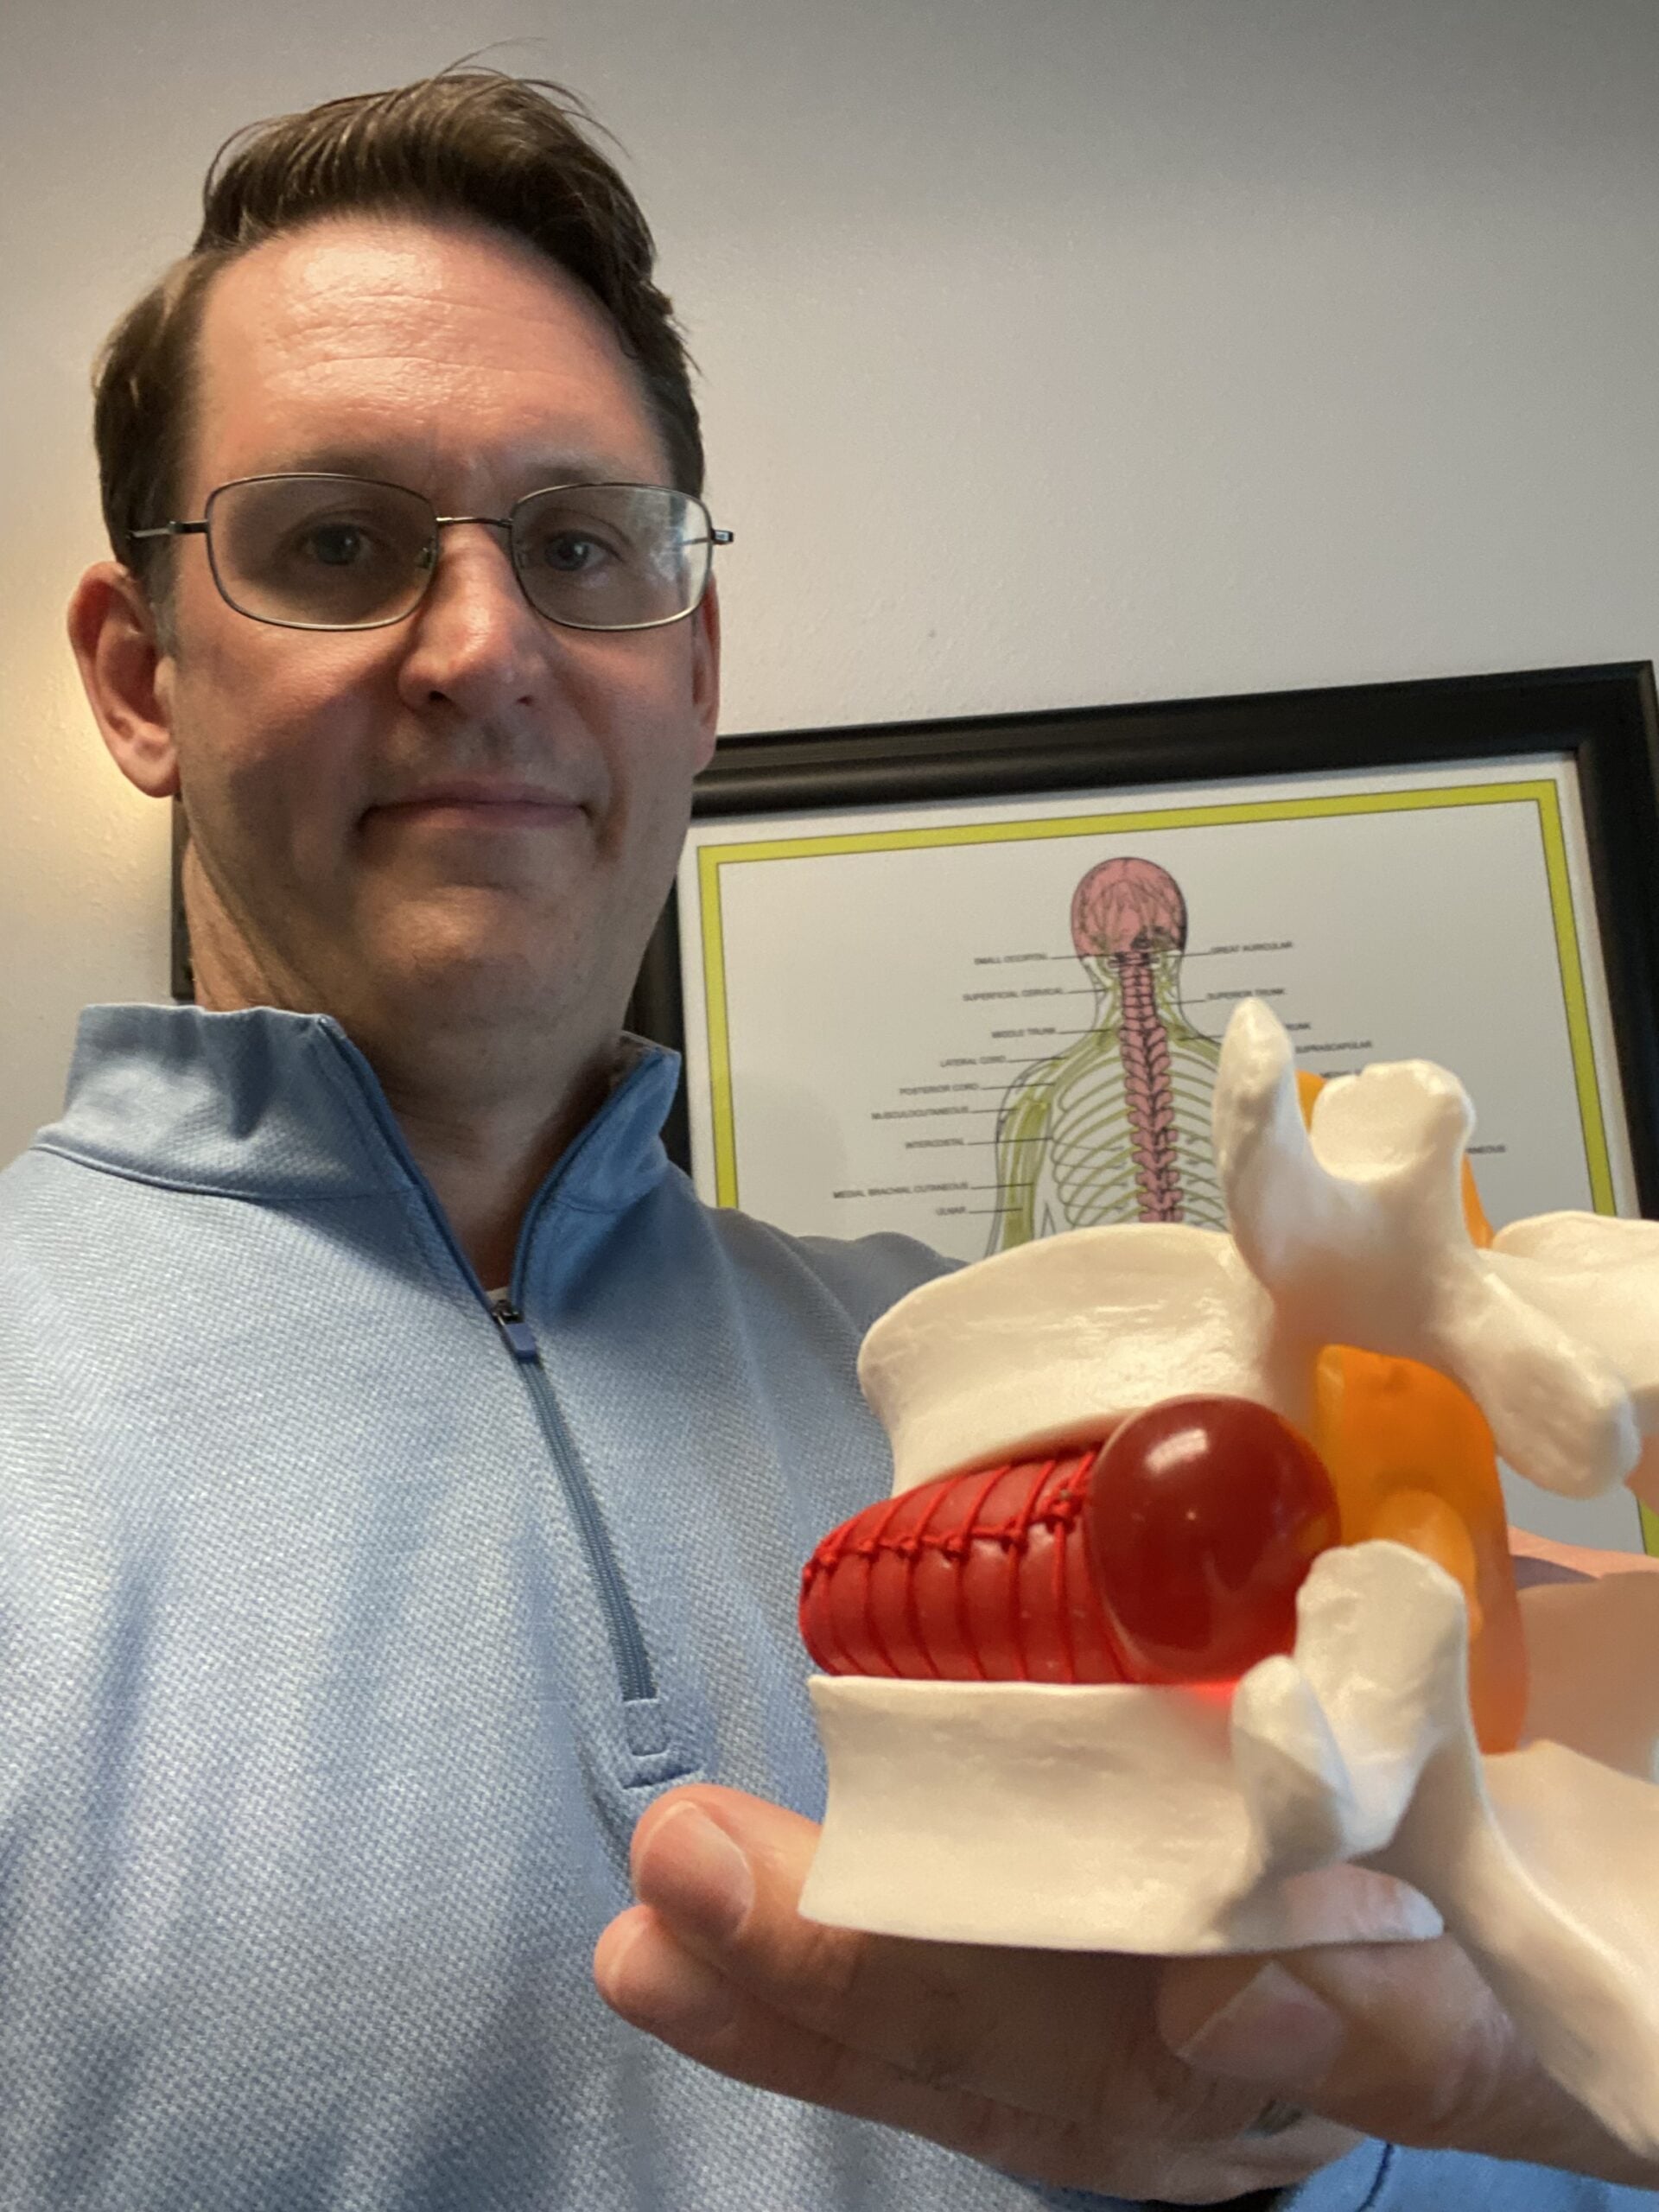
The discs between the lumbar vertebrae help distribute load and allow the lower back to move. Each disc has a tougher outer portion surrounding softer material toward the center. When disc material extends through a weakened or disrupted area of the outer portion, it may be described as a herniation.
A herniated disc can produce local back pain, but the symptoms that often get a patient’s attention occur when a nearby nerve root becomes irritated or compressed. That can create pain, tingling, numbness, or weakness that extends away from the lower back.
The location matters. A lumbar disc problem can produce symptoms through the buttock, thigh, lower leg, or foot depending on which neurological structures are involved.
One of the most common complaints we hear from patients with lumbar disc-related symptoms is that sitting becomes miserable. A desk job may be tolerable for 20 minutes and increasingly uncomfortable after an hour. A long drive can turn into a series of attempts to find a position that does not aggravate the leg.
That pattern is clinically useful information. We want to know whether sitting, standing, walking, bending, coughing, sneezing, or changing positions alters the symptoms. We also want to know whether the pain remains in the back or begins to travel.
Those details help us determine whether the clinical picture behaves like a disc and nerve problem or whether we should be looking elsewhere.
A lumbar disc herniation does not automatically mean a person should stop exercising indefinitely. It does mean that the current phase of the problem matters.
An exercise that is perfectly reasonable for one patient can aggravate another. Heavy loading, repeated flexion, impact, or certain positions may temporarily increase symptoms in some disc presentations. In other cases, appropriately selected movement is an important part of returning to normal function.
We generally prefer modification over fear. The objective is not to convince someone that the spine is fragile. It is to identify what is provoking the current problem, keep the person moving where appropriate, and progressively restore activities as the clinical picture improves.
When an MRI is available, we look beyond the phrase “herniated disc.” We want to know the spinal level, where the disc material is located, whether it is affecting the central canal or an area around a nerve root, whether stenosis is present, and what else is happening at adjacent levels.
Then we compare the scan with the symptoms and examination.
If the imaging shows a finding that corresponds closely with the patient’s pain distribution, sensory changes, weakness, and examination findings, it becomes more clinically meaningful. If the MRI and the patient’s presentation do not line up, we should be cautious about blaming the disc simply because it looks abnormal.
We treat patients, not pictures.
Patients often hear both terms and understandably wonder whether one is worse. A disc bulge generally describes a broader extension of the disc, while a herniation is a more focal displacement of disc material.
Neither term, by itself, tells us how much pain someone should have. A relatively small herniation can be very symptomatic if it affects a nerve in the wrong place, while a larger-looking disc abnormality can sometimes cause surprisingly little trouble.
Severity on paper and severity in real life are not always the same thing.
For appropriately selected patients with a disc or nerve-related presentation, spinal decompression may be considered as part of a non-surgical treatment plan.
Frisco Spinal Rehab uses multiple DRX9000 systems for lumbar and cervical spinal decompression. The DRX9000 provides computer-controlled, programmed traction to a selected spinal region. The treatment rationale is to change mechanical loading around targeted spinal structures and reduce pressure associated with certain disc and nerve-related problems.
We do not tell patients that the DRX9000 magically “puts the disc back in.” We also do not recommend decompression simply because an MRI contains the word herniation. The diagnosis, neurological findings, overall health, symptoms, and treatment goals all matter.
A herniated disc can be the central problem without being the only problem.
Someone who has been avoiding normal movement for weeks may also develop stiffness, weakness, muscular guarding, and poor tolerance for everyday activity. Another patient may repeatedly aggravate the same area because of work demands or training habits.
When appropriate, decompression can therefore be combined with hands-on care, exercise, movement guidance, and other rehabilitation strategies. The mix should depend on the patient rather than on a predetermined package.
Pain scores are useful, but they are not the only measure of progress.
Can the patient sit longer? Is the leg pain traveling less distally? Can he or she get into a car more comfortably? Is walking easier? Is sleep improving? Can the patient begin returning to exercise or work tasks without repeatedly triggering the same symptoms?
Those functional changes often tell us whether a treatment plan is moving in the right direction. If the patient is not progressing as expected, the plan deserves to be reconsidered rather than continued automatically.
Most lumbar disc herniations are not surgical emergencies, but neurological changes matter.
New or progressive significant weakness, loss of bladder or bowel control, numbness in the saddle region, or other major neurological deterioration requires prompt medical evaluation. Severe or rapidly changing symptoms, major trauma, and other concerning findings can also alter the appropriate course of care.
Conservative treatment should never be used to delay necessary medical or surgical evaluation.
Yes. A lumbar disc herniation can irritate or compress a nerve root associated with sciatic symptoms, producing pain and sometimes tingling, numbness, or weakness into the buttock and leg. Sciatica can have other causes as well.
No. Many patients with lumbar disc herniations are managed conservatively, depending on the clinical circumstances. Surgery can be appropriate or necessary in some cases, particularly when neurological findings or other factors warrant it.
Not every exercise is appropriate during every stage of a disc problem, but complete inactivity is not automatically the answer. Exercise selection and progression should be based on the patient’s symptoms, findings, and tolerance.
DRX9000 spinal decompression may be considered for selected patients with disc and nerve-related conditions. Whether it is appropriate depends on the individual case, and results vary.
Not every patient automatically requires new imaging, but MRI can be useful in certain disc and neurological presentations. Existing imaging is most useful when interpreted together with the history and examination.
The pattern of symptoms, neurological findings, physical examination, and imaging when indicated can help determine whether a lumbar disc or nerve root is likely involved. Leg pain alone does not prove a disc diagnosis.
If a lumbar herniated disc is interfering with sitting, work, exercise, sleep, or everyday movement, the first step is determining whether the disc finding actually explains the symptoms and whether conservative care is appropriate.
Frisco Spinal Rehab has treated spine and disc-related conditions in Frisco for approximately 25 years and uses multiple DRX9000 systems for spinal decompression. Our goal is not to put every patient with a herniated disc through the same protocol. It is to understand the clinical picture, determine whether decompression belongs in the plan, and recognize when a different approach is needed.


